scott@vtx-cpd.com

Forum Replies Created
-
AuthorPosts
-
Replying to Kate Green 06/11/2026 - 09:00
Hi Kate,
Of course! Unfortunately, I can’t attach documents directly to the forum, but I’ve summarised Janette’s guidance below. She’s one of our anaesthesia team and has put together a really useful practical guide to vasopressors and positive inotropes, including drug selection, dose ranges, preparation calculations and safety considerations.
Please let me know the best email and I will share the whole document with you.
General considerations
Before treating hypotension, it’s important to confirm that the blood pressure reading is reliable and assess anaesthetic depth, heart rate and rhythm, volume status, ventilation and underlying disease. The choice of drug should reflect the likely cause of hypotension rather than simply treating the blood pressure reading.
Janette also emphasises having a second person independently check all CRI calculations, drug concentrations and pump settings. Syringes should be clearly labelled, IV catheter placement confirmed and a dedicated infusion line used wherever possible to avoid accidental bolus administration. Extension-set dead space is also important, particularly at low infusion rates, as it can delay drug delivery.
Dopamine
Dopamine has dose-dependent effects on heart rate, myocardial contractility and systemic vascular resistance. At approximately 5–10 micrograms/kg/min, its beta-adrenergic effects predominate, increasing heart rate and contractility. Above 10 micrograms/kg/min, alpha-adrenergic effects become more prominent, increasing vascular resistance.
Janette’s suggested dose range is 5–15 micrograms/kg/min by CRI. Dopamine should not be administered as an IV bolus, and patients should be monitored for tachycardia and arrhythmias.
Her document describes an alternative to the standard-concentration approach Kerry suggested. By preparing a weight-adjusted concentration, the infusion rate in mL/hr can correspond directly to the dose in micrograms/kg/min.
For dopamine, the required final concentration is:
Patient weight (kg) × 0.06 = concentration in mg/mL
For example, a 10 kg dog would require a concentration of 0.6 mg/mL. At this concentration, 5 mL/hr delivers 5 micrograms/kg/min and 10 mL/hr delivers 10 micrograms/kg/min.
Using dopamine stock at 40 mg/mL, a 50 mL syringe for this 10 kg patient would contain 0.75 mL dopamine, made up to a final volume of 50 mL with 0.9% saline.
This is particularly intuitive when adjusting the syringe driver, although the concentration must be calculated and prepared individually for each patient. Kerry’s alternative recommendation of a standard 1 mg/mL concentration with a weight-based rate chart may be simpler for teams introducing CRIs.
Dobutamine
Dobutamine primarily stimulates beta-1 receptors and is particularly useful when hypotension is associated with reduced myocardial contractility or cardiac output.
Janette recommends a dose range of 2–10 micrograms/kg/min by CRI. It should not be administered as a bolus. Potential adverse effects include tachyarrhythmias and bradyarrhythmias, and additional caution is needed in cats because of reported neurological adverse effects. It should also be avoided in patients with hypertrophic cardiomyopathy or significant aortic stenosis.
The same weight-adjusted calculation can be used if you want the syringe-driver rate to correspond directly to the dose.
For example, a 10 kg dog would again require a final concentration of 0.6 mg/mL. Using dobutamine stock at 12.5 mg/mL, a 50 mL syringe would contain 2.4 mL dobutamine, made up to a final volume of 50 mL with saline.
At this concentration, 5 mL/hr delivers 5 micrograms/kg/min.
Noradrenaline (norepinephrine)
Noradrenaline is predominantly an alpha-adrenergic agonist and is particularly useful when hypotension is associated with reduced systemic vascular resistance, such as sepsis or significant anaesthetic-induced vasodilation.
Janette gives a dose range of 0.05–1.5 micrograms/kg/min by CRI, with careful titration in small increments. It should not be administered as a bolus. Higher doses can significantly increase afterload and potentially reduce cardiac output.
Unlike dopamine and dobutamine, a fixed concentration with individual weight-based pump-rate calculations is more practical.
Commonly used concentrations are 20 or 40 micrograms/mL.
For example, using noradrenaline stock at 1 mg/mL, adding 2 mL to 48 mL of saline produces a final concentration of 40 micrograms/mL.
For a 10 kg dog receiving 0.05 micrograms/kg/min, the infusion rate would be 0.75 mL/hr.
Ephedrine
Ephedrine has both direct and indirect sympathomimetic effects, increasing myocardial contractility and systemic vascular resistance. Unlike the other drugs discussed, it can be administered as an IV bolus, making it potentially useful when immediate blood pressure support is needed.
Janette recommends 0.05–0.1 mg/kg IV. However, repeated doses can become progressively less effective because of tachyphylaxis, and reflex bradycardia can occur.
Her suggested preparation is to dilute ephedrine to 1.5 mg/mL. If using stock at 30 mg/mL, adding 1 mL to 19 mL of saline produces this concentration.
For a 10 kg dog receiving 0.05 mg/kg, the required volume would be approximately 0.33 mL IV.
Putting this into practice
I think the most important message from Janette, Kerry and Felipe is that standardisation and familiarity are key. Whether you use weight-adjusted concentrations or a fixed concentration with a laminated dosing chart, the aim is to make preparation and administration straightforward enough that clinicians feel confident escalating treatment promptly when indicated.
For a team relatively unfamiliar with CRIs, I would favour starting with one standard dopamine preparation and a simple dosing chart, then gradually introducing the other drugs as everyone becomes more comfortable. Any final protocol should be checked against your available stock concentrations, syringe-driver specifications and local anaesthesia guidance before clinical use.
I hope that helps! Janette’s original document also contains detailed weight-based preparation tables, but hopefully this gives you the main information without needing the attachment.
Scott
Replying to Ruth C. 05/11/2026 - 14:06
Hi Ruth,
That’s really encouraging news! I’m delighted to hear that the ALT and ALP have normalised without further antibiotics or corticosteroids, particularly given how quickly the ALT was increasing previously. I think this supports the possibility that we were seeing residual inflammation following the original bacterial cholangitis rather than persistent infection or a separate chronic inflammatory hepatopathy. The pathologist’s reassessment is also very reassuring. If the fibrosis was genuinely very mild and the overall appearance was predominantly acute bacterial cholangiohepatitis, I would be much less concerned about progressive chronic hepatitis.
Regarding the bile acids, I wouldn’t be overly concerned about an isolated increase to 50 in a clinically well dog with normal ALT, ALP and bilirubin. Bile acids reflect hepatic function and enterohepatic circulation rather than hepatocellular injury, and results can fluctuate depending on feeding status, gall bladder contraction and the timing of sampling. Given the previous cholangitis and considerable gall bladder sludge, some residual disturbance of biliary function would not particularly surprise me. I would certainly take note of the result, but I wouldn’t use it alone as justification for further treatment. I think your plan to repeat the biochemistry and bile acids in another two weeks is entirely reasonable, ideally using a consistent sampling protocol.
I definitely wouldn’t introduce corticosteroids at this stage, even at an anti-inflammatory dose. Although corticosteroids can be useful in selected cases of chronic inflammatory hepatobiliary disease, there isn’t good evidence that a short course prevents progression to fibrosis or cirrhosis following successfully treated bacterial cholangitis. In fact, given the original infectious component, I think we could potentially do more harm than good by introducing immunosuppression without a clear indication. The liver enzymes have normalised spontaneously, the repeat bile culture was negative, and the pathologist feels the original changes were predominantly acute, so I think we have several good reasons to leave things alone for now.
I would continue the Denamarin and ursodeoxycholic acid for the time being, monitor the liver enzymes and bile acids, and consider repeating the ultrasound further down the line to reassess the gall bladder sludge. If everything remains stable, I would gradually extend the monitoring intervals rather than introduce additional treatment. Hopefully this is simply a case where the liver has needed a little longer to recover from a significant infectious insult.
Fingers crossed the next results are equally reassuring!
Scott
Replying to Rosie Marshall 13/10/2026 - 20:33
Hi Rosie, this is a really interesting question, particularly given that this is his third obstruction and surgery isn’t an option. Unfortunately, I think we’re still in fairly unknown territory. The study only evaluated lorazepam for 30 days following a first obstruction, so we really don’t know whether continuing beyond that provides additional protection, or whether there is any benefit to restarting it at the first signs of cystitis.
My feeling is that, in a cat like this with such a high risk of recurrence, I would be quite open to continuing beyond 30 days if he is tolerating it well, although that would be extrapolating beyond the evidence. Equally, using it early during a cystitis flare is physiologically plausible given its skeletal muscle relaxant and anxiolytic effects, but we have no evidence that intermittent treatment actually prevents obstruction. I would be particularly cautious about relying on it once clinical signs develop, as we wouldn’t want to delay assessment of a developing obstruction.
I think this is exactly the sort of patient where a longer course might be worth considering, alongside everything else you’re doing to manage his underlying FLUTD. I’d be really interested to hear how he gets on, particularly whether you notice any improvement in his lower urinary tract signs while receiving it.
Scott 🙂
Replying to Sophie L. 13/10/2026 - 13:04
Hi Sophie,
Thanks for the question. I haven’t personally used the V-Lip-P test extensively, but I think your colleagues are probably correct that it may be more useful than the traditional lipase measurement on a routine biochemistry analyser. The important distinction is exactly what the test is measuring.
Traditional serum lipase activity is not particularly specific for pancreatic disease because lipase activity can originate from tissues other than the pancreas. Consequently, elevations can occur with gastrointestinal disease, renal dysfunction and other systemic illnesses, and I wouldn’t rely on conventional lipase activity alone to diagnose pancreatitis.
The more pancreas-specific assays, such as Spec cPL and SNAP cPL, measure pancreatic lipase immunoreactivity rather than simply total lipase activity. These generally offer better diagnostic specificity, although neither is perfect. There are also newer enzymatic assays, including DGGR-based lipase tests, which have shown reasonable agreement with pancreatic lipase immunoassays in some studies, but they are not necessarily interchangeable.
I would want to check exactly which methodology the V-Lip-P uses before commenting confidently on its accuracy. If it is a DGGR-based assay, I would generally consider it more useful than conventional lipase activity, but I wouldn’t automatically regard it as equivalent or superior to Spec cPL. Different assays have different reference intervals, diagnostic cutoffs and performance characteristics, and agreement between tests does not necessarily mean they have identical sensitivity and specificity for clinical pancreatitis.
The other important point is that no lipase test should be interpreted in isolation. Even pancreatic lipase immunoreactivity can be elevated in dogs without clinically significant pancreatitis, and a normal result does not completely exclude mild or chronic pancreatic disease. I always interpret the result alongside the clinical history, examination findings, other laboratory abnormalities and abdominal ultrasound.
In practice, if I have a dog with compatible clinical signs and a clearly elevated pancreas-specific lipase result, that certainly increases my suspicion of pancreatitis. However, if the clinical picture doesn’t fit, I would be reluctant to diagnose pancreatitis purely on the basis of an elevated lipase measurement.
I’d be interested to know which analyser your practice uses for V-Lip-P, as that would help establish exactly what is being measured and how its diagnostic performance compares with the more established pancreatic lipase assays.
Have a lovely weekend!
Scott 🙂
Replying to Liz Bode 12/10/2026 - 20:51
Thanks Liz, really interesting to hear your thoughts. The cost is pretty eye-watering too, particularly when you factor in the additional monitoring. I think I’m in the same camp as you, potentially worth considering in difficult stage C or stage D cases, but certainly not something I’d be rushing to introduce routinely. Hopefully we’ll see some proper prospective controlled studies before too long!
Scott 🙂
Replying to Ruth C. 29/10/2026 - 17:46
Hi Ruth,
Thanks for the updates on both cases. These are really interesting, particularly the Cockerpoo, and I think the latest results help us considerably in deciding what to do next.
Regarding the Cockerpoo, I think the negative repeat bile culture and unremarkable cytology are encouraging, particularly given that she has now been off antibiotics for several weeks. They don’t completely exclude persistent infection, but they certainly make me less suspicious that ongoing bacterial infection is responsible for the repeated increases in ALT. The negative leptospirosis serology is also reassuring, although I wouldn’t use it in isolation to exclude previous infection.
Having reviewed the full histopathology report, I think there are a few important points. The original changes were very much centred on the portal tracts and bile ducts, with substantial neutrophilic inflammation, neutrophils crossing the biliary epithelium, mild bile duct hyperplasia and periportal fibrosis. That is a fairly convincing histological picture of neutrophilic cholangitis, particularly alongside the original positive E. coli bile culture. Interestingly, there was relatively little inflammation extending into the surrounding hepatocytes, so I would be cautious about automatically interpreting this as conventional chronic hepatitis. The fibrosis certainly suggests some chronicity, but it is predominantly associated with the bile ducts, which could reflect a chronic or resolving cholangitis rather than a separate immune-mediated hepatopathy.
That distinction matters when considering corticosteroids. I agree that we now need to consider whether there is an ongoing inflammatory component that is no longer directly associated with active bacterial infection. However, I wouldn’t regard the negative bile culture alone as sufficient justification for starting immunosuppressive prednisolone, particularly at 2 mg/kg/day. The original histopathology was predominantly neutrophilic rather than lymphoplasmacytic, and we have fairly convincing evidence that the original disease was infectious.
I think your plan to repeat the liver enzymes next week is very sensible. If the ALT is stabilising or starting to decrease, I would be inclined to continue monitoring without introducing additional treatment. If it is continuing to increase substantially, particularly if the dog remains less than completely normal clinically, then I think we need to investigate further rather than simply restarting antibiotics or immediately introducing corticosteroids.
One option would be to ask the original pathologist to review the biopsy in light of the subsequent clinical course and negative repeat bile culture. I would specifically ask whether they consider the changes entirely consistent with bacterial neutrophilic cholangitis or whether there is evidence of a concurrent chronic inflammatory hepatopathy that might justify immunomodulatory treatment. If the liver enzymes continue to increase, repeating liver biopsies may ultimately be the most useful way of establishing what is happening now, because the original biopsy describes the disease at its initial presentation rather than necessarily the process responsible for the current abnormalities.
If we ultimately decide that corticosteroid treatment is appropriate, I would probably be inclined to start more conservatively than 2 mg/kg/day. Depending on the strength of the evidence for sterile inflammatory disease, something around 0.5 to 1 mg/kg/day of prednisolone would be a reasonable initial consideration, with careful monitoring. I would be particularly reluctant to use a full immunosuppressive dose while there remains any meaningful concern about residual infection.
In terms of monitoring, I would repeat biochemistry approximately two weeks after starting treatment, looking particularly at ALT, ALP, GGT and bilirubin, alongside clinical improvement in appetite, energy and general wellbeing. If there is a convincing response, I would then begin a gradual reduction in prednisolone, generally reassessing every two to four weeks. The aim would certainly be to reduce the medication to the lowest effective dose and, ideally, discontinue it completely if possible. Some dogs with genuinely chronic immune-mediated inflammatory hepatopathies require longer-term treatment, but I wouldn’t assume that this patient will need lifelong corticosteroids, particularly if the underlying process was initially triggered by infection.
The ultrasound findings are also interesting. Considerable dependent, mobile gall bladder sludge is not necessarily pathological in itself, and we see this commonly in dogs without clinically significant biliary disease. However, in this particular patient, given the previous E. coli infection and histological cholangitis, I would pay more attention to it. Sludge can be associated with impaired gall bladder emptying and biliary stasis, which may contribute to recurrent ascending infection. I would continue the ursodeoxycholic acid provided there is no evidence of biliary obstruction, and monitor the gall bladder appearance on subsequent ultrasound examinations. The fact that the previous free fluid has resolved is encouraging. I wouldn’t regard the fine echogenic stippling of the liver as particularly diagnostic of anything specific.
Regarding leptospirosis vaccination in this patient, I would be happy for her to be vaccinated again once the current hepatobiliary disease is stable. The negative antibody panel 18 months after vaccination doesn’t necessarily mean that she has no protective immunity, because circulating antibody titres do not always correlate directly with protection. I wouldn’t rush to vaccinate her immediately before potentially starting corticosteroids, however. Given that she is clinically stable, I would prefer to establish what is happening with the liver disease first and then vaccinate once we have a clearer treatment plan and, ideally, she is no longer receiving immunosuppressive doses of prednisolone. If she does require prolonged immunosuppression, the timing and likely effectiveness of vaccination would need to be considered individually.
Regarding your Labrador, that is a very encouraging improvement, particularly the reduction in ALT from 1,900 to 258 and ALP from 700 to 271. I certainly wouldn’t be concerned about having used amoxicillin alongside doxycycline initially, given the severity of the presentation and the uncertainty regarding the underlying diagnosis. However, I would make sure she has completed a full 14-day course of doxycycline if leptospirosis remains a possibility, as that is important for eliminating potential renal carriage.
I agree with your interpretation regarding vaccination. The fact that she developed clinical signs three days after receiving her leptospirosis booster does not establish that the vaccine caused the liver disease, and I would consider a severe vaccine-associated hepatopathy to be very unlikely. Equally, recent vaccination does not completely exclude leptospirosis, particularly if exposure occurred before the booster. Without appropriate diagnostic testing, we cannot establish whether this was leptospirosis, another infectious hepatopathy or an unrelated acute hepatic insult.
I would therefore generally still recommend future leptospirosis vaccination once she has recovered completely. If anything, the possibility that this episode represented leptospirosis reinforces the importance of maintaining protection, particularly in a dog with potential environmental exposure. I would not advise permanently discontinuing leptospirosis vaccination simply because the liver disease developed shortly after a booster. I would, however, make sure the liver enzymes have normalised and that she is clinically well before administering further vaccines.
I think repeating her biochemistry in approximately four weeks is perfectly reasonable given how well she is doing, and continuing Denamarin in the meantime is sensible. If the liver enzymes continue to normalise, I wouldn’t necessarily pursue further invasive investigations. If they increase again, then I agree that repeat ultrasound, bile culture and potentially liver histopathology would become much more important.
So, for the Cockerpoo, I think the main question now is whether the ongoing ALT elevation represents residual biliary inflammation following a successfully treated infection or whether there is a separate chronic inflammatory process developing. I am increasingly less convinced that simply extending marbofloxacin is the answer, but I would also be cautious about moving directly to immunosuppressive prednisolone without further evidence. I think the next blood results, together with a review of the original histopathology, will help determine whether we can continue monitoring or whether further sampling is justified.
Please keep me updated on the next ALT result. I’m particularly interested in whether it continues to increase now that the repeat bile culture is negative.
Scott 🙂
Replying to Ruth C. 20/10/2026 - 13:01
Hi Ruth,
Thanks for the update. The increase in ALT from 128 to 438 in just a week is certainly interesting, and I agree that repeating the ultrasound and bile culture is the most sensible next step. The fact that bilirubin remains normal and GGT is unchanged is encouraging, although the rate of increase in ALT suggests there is ongoing hepatocellular injury that we need to explain.
The signalment is also interesting. Cocker Spaniels are a breed in which we recognise chronic inflammatory hepatopathies, including immune-mediated forms of chronic hepatitis, so that does make me a little more suspicious that there could be an underlying inflammatory component. The original histopathology demonstrated neutrophilic inflammation consistent with ascending bacterial infection, but the periportal fibrosis suggests there may have been a more longstanding process. I would be interested in reviewing the full biopsy report, particularly whether there was any lymphoplasmacytic inflammation, interface hepatitis, hepatocellular necrosis or copper accumulation. The latter is worth considering in a Cocker Spaniel, although it would not explain the positive bile culture on its own.
Regarding your question about the normalisation of liver enzymes with antibiotics, I agree that this is a strong argument for an infectious component, particularly given the initial clinical illness and isolation of E. coli from bile. However, I would be cautious about concluding that the repeated response proves persistent infection. Liver enzymes can fluctuate considerably in inflammatory hepatopathies, and improvement during antimicrobial treatment does not necessarily establish that the antibiotic was responsible. Equally, chronic inflammatory disease and bacterial infection are not mutually exclusive. It is entirely possible that an underlying hepatobiliary disorder is predisposing this patient to recurrent ascending infection. This is why I think repeating the bile culture is so valuable. If you isolate E. coli again, particularly with compatible cytology, that would strengthen the argument for persistent or recurrent infection. If the culture is negative, I would become more suspicious of ongoing sterile inflammation, although recent antibiotic treatment can obviously affect culture sensitivity. The fact that the original cytology showed numerous extracellular rods rather than intracellular organisms does not exclude infection, particularly given the positive culture and compatible liver histopathology.
In terms of leptospirosis, I think it would still be reasonable to investigate, although I would consider it less likely in this particular patient given the confirmed E. coli biliary infection and the relapsing course over several months. At this stage, urine or blood PCR would be less useful for establishing whether leptospirosis caused the original illness in May, particularly following antimicrobial treatment. Serology would be more informative, although interpretation is complicated by vaccination and the time elapsed since the initial presentation. A single positive MAT titre would not necessarily establish active infection, and a negative result this far into the disease would make previous leptospirosis less likely, assuming an appropriate serovar panel. I would not necessarily prioritise leptospirosis testing over repeating the bile culture in this case, but it remains a reasonable consideration.
Your Labrador case is slightly different, and I would be more concerned about leptospirosis there. The acute onset of vomiting, marked liver enzyme elevations and hyperbilirubinaemia are certainly compatible with leptospirosis, even without evidence of renal involvement. We increasingly recognise that some dogs develop predominantly hepatic manifestations. Vaccination reduces the risk of clinical disease but does not completely exclude infection, and I would not rely on a negative in-house SNAP Lepto test to rule it out, particularly early in the course of illness. These tests have limitations in sensitivity, and antibody responses may not yet be detectable during the first few days. Vaccination just three days earlier also makes subsequent serological interpretation more complicated.
For that patient, I would ideally have submitted blood and urine for Leptospira PCR before starting antibiotics, together with MAT serology, recognising that early serology can be negative and may need repeating after 7 to 14 days. Given that doxycycline has already been started, PCR sensitivity may now be reduced, but I would still consider diagnostic testing depending on the clinical course. I would definitely extend the doxycycline to a full 14-day course if leptospirosis remains a realistic possibility. Seven days would not be my preferred duration because we want to eliminate renal carriage as well as treat the systemic infection. The usual doxycycline dose is 5 mg/kg twice daily or 10 mg/kg once daily for 14 days.
Regarding the case in my lecture, the important distinction is that doxycycline is the treatment directed specifically at leptospirosis. Amoxicillin clavulanate is not routinely required alongside it simply because the liver enzymes are elevated. If there is independent evidence suggesting bacterial cholangitis or another bacterial infection, then additional antimicrobial coverage may be justified, but otherwise I would be comfortable using doxycycline alone once the patient can tolerate oral medication. In severely affected hospitalised patients unable to tolerate doxycycline, an intravenous penicillin-based antibiotic can initially be used, followed by doxycycline to eliminate renal carriage.
Returning to your Cocker Spaniel, I think CT could potentially be useful, particularly if you are concerned about an underlying structural biliary abnormality that is not apparent on ultrasound. CT may help identify biliary dilatation, cholelithiasis, pancreatic or duodenal abnormalities, or other structural changes that could predispose to recurrent infection. However, if your colleague is experienced with ultrasound and the gall bladder and biliary tree can be assessed adequately, I would probably prioritise repeat ultrasonography and bile culture before proceeding to CT. CT is not necessarily going to identify microscopic cholangitis or explain the inflammatory changes seen on biopsy, and I would be reluctant to pursue it simply because the ALT is increasing.
If the repeat bile culture is positive, I would treat according to the new susceptibility results and consider a longer course of antibiotics, potentially eight to twelve weeks, with biochemical monitoring during treatment and after discontinuation. If it is negative and the ALT continues to rise, I would seriously consider whether we are dealing with an underlying chronic inflammatory hepatopathy. At that point, reviewing the original histopathology and potentially obtaining further liver biopsies would be worthwhile before introducing corticosteroids. I would be particularly cautious about immunosuppression until we have reasonably excluded ongoing bacterial infection.
I think the most important thing now is not to assume that this dog needs marbofloxacin indefinitely. The initial infectious diagnosis was convincing, but the fibrosis, breed predisposition and repeated biochemical relapses raise the possibility of a more complicated underlying process. Hopefully the repeat bile culture will help us distinguish between persistent infection and ongoing inflammation.
Do let me know what the ultrasound and culture show. I am particularly interested in whether the same organism is isolated again, as that would significantly influence how I approached the next stage of treatment.
Have a wonderful weekend.
Scott 🙂
Replying to Silvana S. 23/10/2026 - 09:51
I am so glad you enjoyed it!
Let me know if you have any topic suggestions for sessions like this that we hold in the future.
Scott 🙂
Replying to Silvana S. 15/10/2026 - 10:28
Hello!
I hope you are well. Andy is in the process of editing the recording.
I will let you know when available.
Scott 🙂
Hi Ruth,
Thanks for sharing this case. I can understand your frustration, particularly as you’ve done a really thorough investigation, established a diagnosis with histopathology and bile culture, and demonstrated a good response to antimicrobial treatment, only to see the liver enzymes increase again once antibiotics are discontinued.
I would also be interested to know a little more about the patient. What is the signalment, particularly the breed, age and sex? Have you investigated leptospirosis, and were any concurrent gastrointestinal or pancreatic abnormalities identified? I would also be interested in whether the original bile cytology identified intracellular bacteria or whether the organisms were predominantly extracellular, and whether the gall bladder sediment has changed on subsequent ultrasound examinations.
I think the first thing to say is that this is a fairly convincing case of bacterial neutrophilic cholangitis or cholangiohepatitis. The acute presentation, particularly the fact that the dog was clinically unwell, together with the marked increases in ALT and bilirubin, certainly suggests an infectious component. The histopathology showing predominantly neutrophilic periportal inflammation, together with the isolation of E. coli from bile, makes an ascending bacterial infection very likely. The repeated biochemical improvement with antibiotics also supports this, although we have to be careful about assuming that every subsequent increase in ALT necessarily represents recurrence of infection.
I think all the treatment you’ve provided so far has been entirely appropriate, including the initial use of Synulox and subsequently the introduction of a fluoroquinolone. The initial culture demonstrated susceptibility to both drugs, and the improvement in liver enzymes following treatment was encouraging. I certainly wouldn’t look at this case and think that you should have managed the initial presentation differently.
One thing that interests me is the speed with which the liver enzymes have increased following discontinuation of antibiotics. After the initial 10 day course of Synulox, the ALT increased quite dramatically, and something similar happened after the six week course. That makes me wonder whether the infection was ever completely eliminated or whether there is an underlying biliary abnormality allowing infection to persist or recur. However, I think there is another possibility here that is equally important to consider.
The biopsy findings are particularly interesting because, although the neutrophilic component supports an acute infectious or inflammatory process, the presence of periportal fibrosis suggests that there may also be a more chronic component to the disease. We sometimes see patients that initially present with quite dramatic acute hepatobiliary disease, but subsequently develop persistent inflammation even after the original insult has resolved. That is probably what I would be most suspicious of in this case, particularly given the repeated biochemical response to treatment followed by further increases in ALT.
One of the main points I always try to emphasise with acute liver disease is that an acute insult does not necessarily mean the problem will remain entirely acute. There is always the possibility of ongoing inflammation and, in some cases, progression towards chronic hepatobiliary disease. The original bacterial infection may have been the initiating event, but it does not necessarily follow that bacteria are responsible for every subsequent increase in liver enzymes. We could now be dealing with an ongoing inflammatory response that is no longer directly associated with active infection.
In terms of antimicrobial duration, yes, some of these cases do require prolonged treatment. For bacterial neutrophilic cholangitis, I generally recommend a minimum of six to eight weeks of culture directed antimicrobial therapy, and occasionally longer depending on the clinical and biochemical response. Courses extending to two or even three months are certainly not unheard of, particularly in complicated cases where infection is difficult to eradicate. However, I would be reluctant to simply prescribe another three months of marbofloxacin without first considering why the abnormalities keep returning. Although the E. coli was reportedly susceptible to both amoxicillin clavulanate and marbofloxacin, susceptibility in vitro does not necessarily guarantee eradication of an infection within the biliary system, particularly if there is impaired bile drainage, inspissated bile, or an underlying structural abnormality.
I would be interested in reviewing the original ultrasound findings in more detail, particularly the appearance of the gall bladder wall, common bile duct and intrahepatic biliary tree. You mentioned some inspissated bile and a small amount of free fluid adjacent to the liver. Neither finding necessarily establishes significant biliary disease, but in a patient with recurrent bacterial cholangitis I would want to reassess these structures carefully. I would also be interested in whether there was any evidence of gall bladder mucosal hyperplasia, cholelithiasis, biliary dilatation or changes involving the pancreas or proximal duodenum that might contribute to ascending infection.
The other thing I would seriously consider is repeating the cholecystocentesis rather than continuing to alternate between Synulox and marbofloxacin. I appreciate that this may seem a little concerning given the previous infection and the possibility of introducing further complications, but I think it could be very valuable here. We know E. coli was present initially, but we do not know whether it is still present, whether a different organism has subsequently become involved, or whether the biliary infection has actually resolved and we are now dealing with residual or recurrent sterile inflammation.
If you are contemplating another prolonged course of antibiotics, I would much rather establish whether bacteria are still present. Repeating bile cytology and aerobic and anaerobic culture would be a relatively less invasive way of investigating this compared with repeating liver biopsies, assuming the gall bladder is suitable for safe sampling. It would also allow you to confirm that you are still using an appropriate antibiotic rather than assuming the original susceptibility pattern remains relevant. Ideally, I would obtain those samples before restarting antimicrobials, provided the patient remains clinically stable.
If the repeat bile culture is positive, then I think there is a reasonable argument for another prolonged course of appropriately selected antibiotics, potentially extending to eight to twelve weeks depending on the findings and response. I would also want to investigate whether there is an underlying reason why the infection is persisting. If the culture is negative, particularly if the cytology is also unremarkable, then I would become increasingly suspicious that we are dealing with a more chronic inflammatory hepatobiliary process rather than persistent bacterial infection. Of course, a negative culture does not completely exclude infection, particularly following recent antimicrobial treatment, but it would certainly influence my thinking.
Regarding the most recent results, an ALT of 128 is a very different situation from an ALT of 1,349, particularly if the dog is clinically well and the bilirubin has normalised. Assuming 128 represents only a mild elevation relative to your laboratory’s reference interval, I would not automatically restart marbofloxacin at this stage. I would be inclined to repeat the biochemistry in approximately one to two weeks, ideally including ALT, ALP, GGT and bilirubin, to establish whether this is genuinely increasing again or simply a small residual fluctuation following treatment. I think there is a reasonable chance that we may be overinterpreting a relatively minor elevation given the severity of the previous abnormalities.
If the ALT is clearly increasing again, particularly if we start seeing accompanying increases in bilirubin or cholestatic enzymes, then I would be much more concerned about ongoing hepatobiliary disease. At that point, I would favour repeat abdominal ultrasound and, if appropriate, repeat bile sampling for cytology and aerobic and anaerobic culture before committing to another prolonged antimicrobial course.
I would also continue the Denamarin and Destolit for now. I am comfortable using these together, provided there is no evidence of complete extrahepatic biliary obstruction. Ursodeoxycholic acid may be particularly useful here because of its choleretic properties, although obviously it is not going to eliminate an established bacterial infection on its own.
The other consideration, and perhaps the most important one for me, is whether we now need to think about treating an underlying chronic inflammatory component. The periportal fibrosis on histopathology suggests chronicity, and although the neutrophilic inflammation is consistent with an ascending bacterial process, it does not necessarily exclude an ongoing inflammatory response after the infection has resolved.
If we can reasonably exclude persistent infection, then I think there may be a role for introducing anti-inflammatory corticosteroid therapy rather than continuing antibiotics indefinitely. I would not necessarily jump straight to prednisolone at this stage, because I would be uncomfortable introducing immunosuppression while there is still a realistic possibility of active bacterial infection. However, if repeat bile culture is negative and the liver enzymes continue to increase, I think that becomes a reasonable discussion.
We do occasionally encounter patients where the original insult appears to have been infectious, but the subsequent clinical problem is ongoing inflammatory hepatobiliary disease. In those circumstances, continuing to prescribe antibiotics may not address the underlying pathology. A carefully monitored trial of anti-inflammatory treatment could potentially be more useful, although I would want to be reasonably confident about the diagnosis before taking that approach.
You could also consider repeating the liver biopsy, particularly if the abnormalities become more significant or the diagnosis remains uncertain. That would allow you to determine whether the original neutrophilic inflammation has resolved, whether there is now a more chronic lymphoplasmacytic or mixed inflammatory infiltrate, and whether the fibrosis has progressed. It would also help establish whether corticosteroid treatment is justified. Obviously, repeating a biopsy is more invasive, and I appreciate there may be financial considerations, so I would probably favour repeating cholecystocentesis first if the patient is otherwise doing well.
One other question I have is whether you have tested for leptospirosis. I appreciate that the isolation of E. coli from bile and the histopathology make ascending bacterial cholangitis the leading diagnosis, but given the severity of the original hepatocellular injury and hyperbilirubinaemia, I would still be interested in whether leptospirosis was investigated or excluded. It would not be my leading differential at this stage, but I think it is worth considering in a dog with such a dramatic initial hepatic presentation.
I would also be interested to know whether the original bile cytology identified intracellular bacteria or whether the organisms were predominantly extracellular. You mentioned that numerous bacteria were present without significant active inflammation, which is interesting, particularly given the neutrophilic inflammation identified on liver histopathology. I would also be interested in the dog’s breed and age, whether any concurrent gastrointestinal or pancreatic abnormalities were identified, and whether the gall bladder sediment has changed on subsequent ultrasound examinations.
So, if this were my patient, and assuming she is currently clinically well, I would hold off restarting marbofloxacin, repeat the liver enzymes in one to two weeks, and see what direction things are moving. If they remain stable or normalise, I would continue monitoring. If they increase substantially again, I would investigate for persistent biliary infection rather than automatically prescribing another three months of antibiotics.
If repeat cholecystocentesis confirms persistent infection, then a further prolonged course of culture directed antibiotics would be appropriate. If it does not, then I think we need to seriously consider whether we are dealing with a chronic inflammatory process that may ultimately require anti-inflammatory treatment rather than continued antimicrobial therapy.
I certainly wouldn’t regard this as a treatment failure on your part. You’ve established the diagnosis and obtained a very good response to treatment. The challenge now is determining whether we are dealing with an incompletely resolved infection, repeated ascending infection, or residual hepatobiliary inflammation. Those are slightly different problems, and I think distinguishing between them is going to be much more useful than simply extending the antibiotic course indefinitely.
Let me know how the next set of bloods looks. I’d be interested to hear how this one progresses, particularly whether you have investigated leptospirosis and whether repeating the bile culture might be an option.
Scott 🙂
Hi Kirsten,
I’ve had another really helpful response from Felipe, one of our anaesthesia specialists, and thought I’d pass on his thoughts as well. Interestingly, his recommendations are very similar to Kerry’s, which is reassuring.
He is also a big advocate of encouraging teams to treat hypotension proactively rather than delaying treatment because they are unfamiliar with vasoactive drugs or the calculations involved.
For relatively healthy patients requiring blood pressure support under GA, dopamine is his usual first choice, whereas he prefers dobutamine when there is a particular concern about myocardial contractility or cardiac output.
He also suggested that ephedrine might be a useful drug for teams to become familiar with initially, as it can be administered as an IV bolus, much like atropine or glycopyrrolate. The limitation is that some patients respond poorly, and repeated doses often become less effective because of tachyphylaxis.
Regarding your original question about simplifying syringe-driver calculations, he agrees that this is absolutely the right approach. His preference is to use a standard drug concentration alongside a simple weight-based dosing chart rather than preparing different concentrations for individual patients.
He uses dopamine at 400 micrograms/mL, compared with Kerry’s 1 mg/mL, but the principle is exactly the same. He suggested creating a spreadsheet with patient weights across the columns and doses down the rows, allowing staff to look up the appropriate mL/hr without having to calculate anything during the anaesthetic.
For dopamine, he suggested starting at 5 micrograms/kg/min and adjusting by 1–2 micrograms/kg/min every 2–5 minutes according to the blood pressure response and the patient’s cardiovascular status. He also pointed out that dopamine and dobutamine could potentially use the same dosing chart if prepared at the same concentration, although their clinical indications and appropriate dose ranges still need to be considered separately.
His main message was that getting everyone comfortable with one standard preparation and a straightforward dosing chart would probably be more valuable in the long term than trying to make the number on the syringe driver correspond directly to the dose.
It’s been interesting getting several anaesthetists’ perspectives on this, and there is considerable agreement between them. I think you now have a good foundation for developing something practical for your team.
Hope this is helpful, and do keep me posted on how you get on!
Scott
Replying to Kirsten Hearn 09/10/2026 - 16:58
Hi Kirsten,
Just a further update on this. I’ve also heard back from Janette, another member of our anaesthesia team, who has kindly put together a really useful seven-page document covering the preparation and administration of dopamine, dobutamine, norepinephrine and ephedrine.
It includes practical dilution tables based on patient weight, suggested dose ranges, worked calculations and guidance on choosing the appropriate drug depending on the underlying cause of hypotension. She has also included some important safety considerations around preparing and administering CRIs.
One of the approaches she outlines is adjusting the concentration according to patient weight so that the number displayed on the syringe driver in mL/hr corresponds directly to the dose in micrograms/kg/min, which is very much what you were originally hoping to achieve. Her tables currently use 100 mL preparations, so these would need adapting for your 50 mL syringes.
I think you’ll find it really useful alongside Kerry’s suggestions, particularly when developing your own protocol.
If you can let me know the best email address to reach you on, I’ll happily send you a copy of Janette’s document.
Scott x
Replying to Kirsten Hearn 09/10/2026 - 16:58
You’re very welcome, Kirsten! I’m glad it was helpful. I think having a straightforward, standardised protocol will make a real difference to everyone’s confidence in managing these cases. I’ve also asked a few other colleagues for their thoughts, so I’ll let you know if I receive any further suggestions. Do let me know how you get on, and if any other questions come up, we’re always happy to help.
Scott
Hi Kirsten,
I spoke to one of our ECC team about this. Her feeling was that, particularly for a team that is relatively new to vasoactive CRIs, dopamine is a very sensible place to start. It has a rapid effect, is easy to titrate, is inexpensive and is generally readily available.
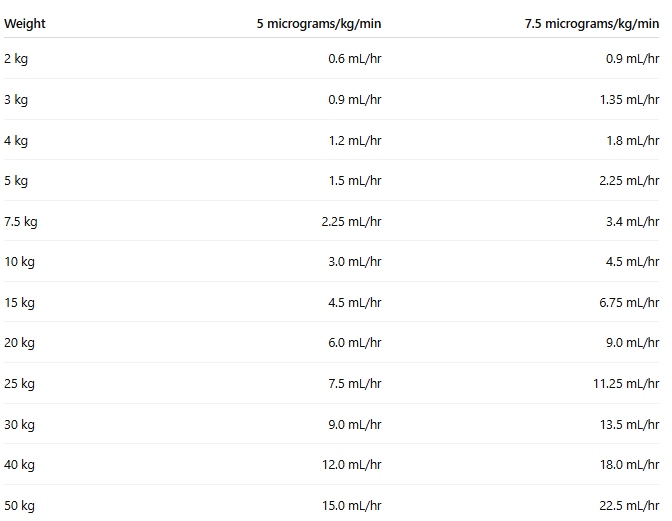
She suggested standardising your dopamine CRI to a final concentration of 1 mg/mL. You can make that up in your 50 mL syringe driver; the actual volume of stock dopamine you add will obviously depend on the concentration of the product you have.
For routine hypotension under GA, she keeps the dopamine range quite simple at 5–7.5 micrograms/kg/min, starting at 5 and titrating according to the blood pressure response.
At a final concentration of 1 mg/mL, the calculation is:
mL/hr = bodyweight (kg) × dose (micrograms/kg/min) × 0.06
So you could make a simple laminated chart beside the syringe driver:

The important bit before reaching for the CRI is still to assess why the patient is hypotensive: anaesthetic depth, volume status, heart rate/rhythm, ventilation and underlying disease, rather than treating the blood pressure number in isolation.
She tends to reserve dobutamine for situations where poor contractility/cardiac dysfunction is specifically suspected, rather than using it routinely for uncomplicated GA hypotension. If you can get norepinephrine/noradrenaline, she felt it was definitely worth having available, particularly when vasodilation/vasoplegia is the predominant problem, such as in septic patients. She also uses ephedrine, although was a little more cautious about introducing that initially to teams with less experience of these drugs.
I think your idea of standardising this is excellent. Having one standard dopamine concentration and a laminated weight/rate chart beside the driver removes most of the maths at exactly the point when people don’t want to be doing calculations!
I hope that helps.
Scott 🙂
Hi,
Thanks for the question. This makes complete sense, and I can see exactly what you are trying to achieve with making the CRIs much more straightforward and practical for everyone to use.
Let me speak to our anaesthesia team and get their thoughts on the best way to structure the dilutions and template, and I will get back to you!
Scott 🙂
-
AuthorPosts